
Telemedicine and virtual care platform development, built and run by the same team
Digital Scientists builds and runs telemedicine and virtual care platforms: HIPAA-compliant video and phone visits, triage and care-team consoles, provider routing, devices and EHR integration. We built NeverAlone as a 90-day MVP, and we still operate it: 30,000 patients across six states, 100,000+ calls a year, and a licensed provider reached in under 3 minutes. Most clients start with a Blueprint that maps the care model, the integrations and the build plan before any code is written.
Updated
Patients across six states on NeverAlone
Virtual care calls a year
To reach a licensed provider, 24/7
Treat-in-place rate






Telehealth is one component. A virtual care platform is the connected system.
A virtual care platform is the technology that delivers care wherever the patient is. Acute and ambulatory settings, post-acute and skilled nursing, home health and hospice, behavioral health, and rural populations who cannot reach specialty care without a 90-minute drive. It connects four moving parts: synchronous telehealth (video and messaging visits), remote patient monitoring (continuous device data from blood pressure cuffs, glucometers, pulse oximeters, and continuous monitors), AI-powered virtual care assistants (routine monitoring, medication management, escalation triage), and EHR and payer integration so the data flows where care decisions get made.
Buying a video tool is not the same as building a virtual care platform. Video is the easy part. The hard parts are the workflow integration, multi-state licensing logic, payer billing alignment, RPM data routing, and the operational discipline to run all of it in production every day. We have been doing exactly that for 30,000 patients across six states since the platform first went live.
Three layers, one platform.
A virtual care platform that works in production has three layers. We have built and operated all three. Skipping any of them is the most common reason custom virtual care builds stall in pilot and never reach production.
Care Delivery Model
Synchronous telehealth, asynchronous messaging, after-hours triage, family communication, and care plan adherence. Multi-state licensing logic, payer billing rules, and the workflow that connects clinicians to patients across modalities.
Connected Devices & RPM
Continuous data from blood pressure cuffs, glucometers, pulse oximeters, weight scales, and wearables. Routing rules, alert thresholds, escalation paths, and the data engineering that turns device noise into clinical signal.
AI Virtual Care Assistants
Routine monitoring, medication management, after-hours triage, and intelligent escalation. Provider-driven, not vendor-driven.
What does a virtual care platform look like after five years in production?
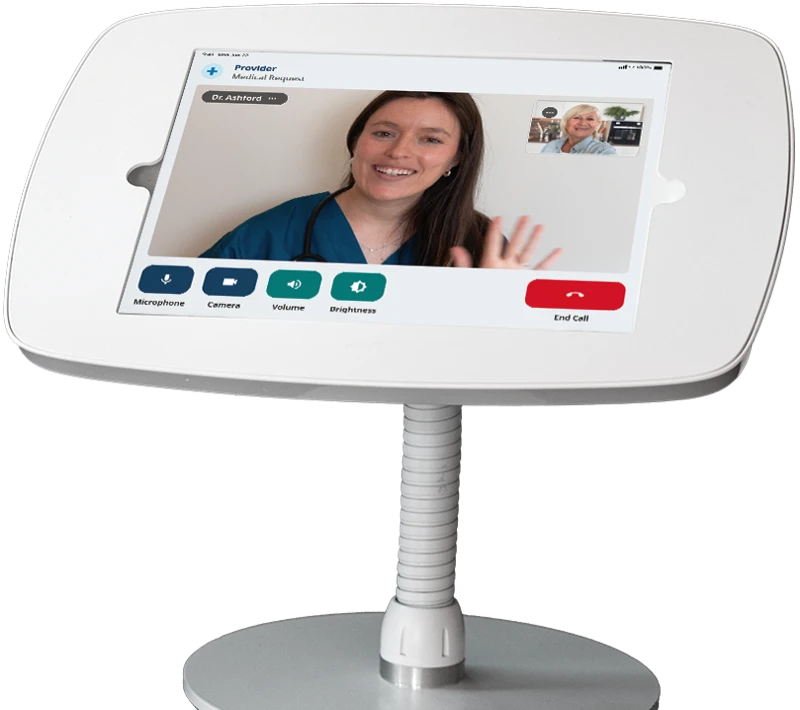
It looks like NeverAlone: a 24/7 virtual care platform that connects seniors, post-acute residents and people with intellectual and developmental disabilities to a licensed provider by video. Digital Scientists built it for CommuniCare as a 90-day MVP, and we still run it.
It went live in March 2021 as a one-touch tablet for independent-living seniors. Every step after that was earned by the step before: skilled nursing, IDD, employee health, then home health, hospice and behavioral health by August 2023. Today it runs on 750+ devices, handles 100,000+ calls a year and holds a 96% treat-in-place rate, so most after-hours problems get solved where the resident is instead of in an emergency room.
Patients, six states
Devices in the field
Treated in place

Skilled nursing, after hours
The night nurse used to remember a different phone number for every need. Now one console reaches a provider in under 3 minutes.
Independent living and IDD
No username and no password. One touch on the tablet connects the resident to a care partner by video.
New care settings
Home health, hospice and behavioral health run on the same platform, added as each pilot proved its value.
When does an off-the-shelf telehealth tool stop fitting?
When virtual care stops being a side channel and becomes the product or a core service line. A licensed video tool is fine for occasional visits. It stops fitting when you need your own triage, provider routing, device fleet, EHR data and reporting.
Generic telehealth software makes clinical teams adapt to the tool. That works until the workflow is the thing that matters: who answers at 2 a.m., which provider is licensed for this patient's state, what the provider sees before saying hello, and where the record of the visit ends up.
Plenty of organizations should buy. The table shows where the line usually falls. If you are not sure which side you are on, a Blueprint answers it before you commit to either.
Off-the-shelf telehealth tool versus a custom virtual care platform
| Question | Off-the-shelf telehealth tool | Custom virtual care platform |
|---|---|---|
| How fast can we start? | Days, once the license is signed | Weeks to a working MVP. NeverAlone went from start to pilot in 90 days |
| Does it fit our care model? | Your team adapts its workflow to the tool | Triage, routing and escalation are built around how your team already works |
| Where does the data live? | In the vendor's system | In your cloud account and your EHR |
| What can it connect to? | What the vendor already supports | Any system with an API, a standard interface or a reliable export |
| Who owns it? | You rent it | You own the code and the IP |
| Best when | Video visits add to in-person care | Virtual care is your product, your service line or something you sell to others |
Common patterns, not rules. Some clients run a licensed tool for routine visits and build only the piece that sets them apart.
Who runs the platform after launch?
We do. We operate the virtual care platform we build. NeverAlone has run 24/7/365 since March 2021, with Digital Scientists handling monitoring, releases, security updates and L2/L3 support while the care team answers the calls.
A virtual care platform is a live service, not a finished project. Tablets lose Wi-Fi, carriers change, browsers update, and someone has to notice before a resident can't reach a nurse at night. On NeverAlone we manage the device fleet with mobile device management, watch call quality and queue times, and ship changes without taking the service down.
We support platforms we built. Your team or a clinical partner takes first-line questions, and we take L2 and L3. When you're ready to own it, we hand over the code, the cloud accounts and the runbooks on a build-operate-transfer plan. See platform operations.
NeverAlone in production since March 2021
From request to a licensed provider
Managed devices in the field
How does a virtual care visit move through the platform?
A request comes in from a tablet, a phone or an app, gets triaged, and routes to a provider licensed to see that patient. On NeverAlone that takes under 3 minutes, 24 hours a day.
Request
One touch on a tablet with no login, a phone call, or a patient app.
Triage
Clinical or non-clinical, so the right person picks it up.
Route
Only to providers certified in the patient's state. The platform tracks each provider's state licenses.
Visit
HIPAA-compliant video, with history, medications and diagnoses on screen beside the call.
Escalate and document
E911 when it's an emergency. An AI scribe drafts the note for the clinician to review.
Telemedicine capabilities built for clinical adoption.
HIPAA-Compliant Video
Secure, high-quality video conferencing designed for clinical encounters with multi-party support.
EHR Integration
Patient history, medications and diagnoses flow in from the EHR, so the provider sees the chart during the visit.
Intelligent Scheduling
Smart scheduling and routing that matches patients with appropriate providers based on need and availability.
Device Integration
Connect peripheral devices for vital signs, diagnostics, and monitoring during virtual visits.
Clinical Documentation
Integrated documentation with templates and AI assistance to capture complete visit information.
Analytics & Reporting
Utilization tracking, outcomes measurement, and quality reporting dashboards.
What does a telehealth platform need to connect to?
Video, phone, emergency services, the EHR and the devices patients actually use. We can integrate with any system that has an API, a standard interface or a reliable export, and on NeverAlone these run in production today.
HIPAA-compliant video conferencing is less about the video and more about the setup around it: a vendor that signs a BAA, encryption in transit, access controls, and an audit trail of who joined which visit. We build video and voice on the AWS Chime SDK inside a HIPAA-eligible AWS account, with Bandwidth for E911 and Twilio for text messages and one-time codes.
EHR data from PointClickCare and Netsmart (GEHRIMED) flows into NeverAlone, with patients matched across EHRs, so the provider sees the chart during the call. See healthcare integrations, contact center and telephony and security and PHI.
Video and voice
AWS Chime SDK
Emergency calling
Bandwidth E911
Messaging
Twilio texts and one-time codes
EHRs
PointClickCare, Netsmart (GEHRIMED)
Devices
Managed tablets and phones
Documentation
HealthContext.AI ambient scribe
Call center
Queues, multi-way calls, surveys
Reporting
Call and utilization dashboards
What does an automated remote patient monitoring platform need?
Readings that arrive on their own, rules that decide which ones need a person, and a care team that acts from the same console it uses for video visits. Remote patient monitoring (RPM) is collecting health data such as blood pressure, heart rate and oxygen levels from patients outside the clinic and routing it to clinicians.
Most RPM programs stall after the device ships. Readings pile up in a vendor portal nobody opens, and alerts fire on every out-of-range number. We build monitoring into the virtual care platform instead, so a reading lands next to the patient's chart and the provider sees vitals beside the video call. On NeverAlone that console serves 30,000 patients across six states on 750+ managed devices, with 96% treated in place.
Devices connect the way any system does: through an API, a standard interface or a reliable export. In 2021 we prototyped linking participants' Fitbit and Withings accounts to NeverAlone, pulling activity data into charts for the care team. Reading device data accurately is work we've shipped before: Guardian reads vital signs off operating room monitors with 99.9% accuracy.
- Collect. Readings from home devices, tablets and vendor platforms, matched to the right patient.
- Filter. Rules set per patient and condition decide what needs a person. The rest is charted.
- Act. A nurse or provider follows up by video from the same console, with E911 when it's an emergency.
- A person decides. Software flags, a clinician decides, and every alert and response is logged.

The NeverAlone provider console: patient details, vital signs and the assessment sit beside the video call, so the provider decides with the data in view.
Telemedicine applications that transform care delivery.
After-Hours Coverage
24/7 physician access for SNFs and care facilities, reducing unnecessary ER transfers and enabling immediate clinical decisions when issues arise outside normal hours.
Outcome: Fewer transfers, better outcomes, cost savings.
Specialist Consultations
Connect patients with specialists regardless of geography. Cardiology, neurology, psychiatry, and other specialists available virtually when needed.
Outcome: Improved access, faster diagnosis.
Virtual Primary Care
Extend primary care services to home-bound patients or rural populations. Regular check-ins, medication management, and preventive care delivered virtually.
Outcome: Expanded reach, new revenue streams.
Behavioral Health
Psychiatric and counseling services delivered via secure video. Reduces stigma, improves access, and enables consistent care for mental health conditions.
Outcome: Better mental health access and outcomes.
Post-Discharge Follow-Up
Structured virtual follow-ups after hospital discharge to monitor recovery, adjust medications, and prevent readmissions.
Outcome: Reduced readmissions, better transitions.
Value-Based Care Enablement
Telemedicine as infrastructure for VBC programs, enabling regular touchpoints, chronic care management, and quality measure achievement.
Outcome: Quality incentives, shared savings.
Where do most virtual care projects start?
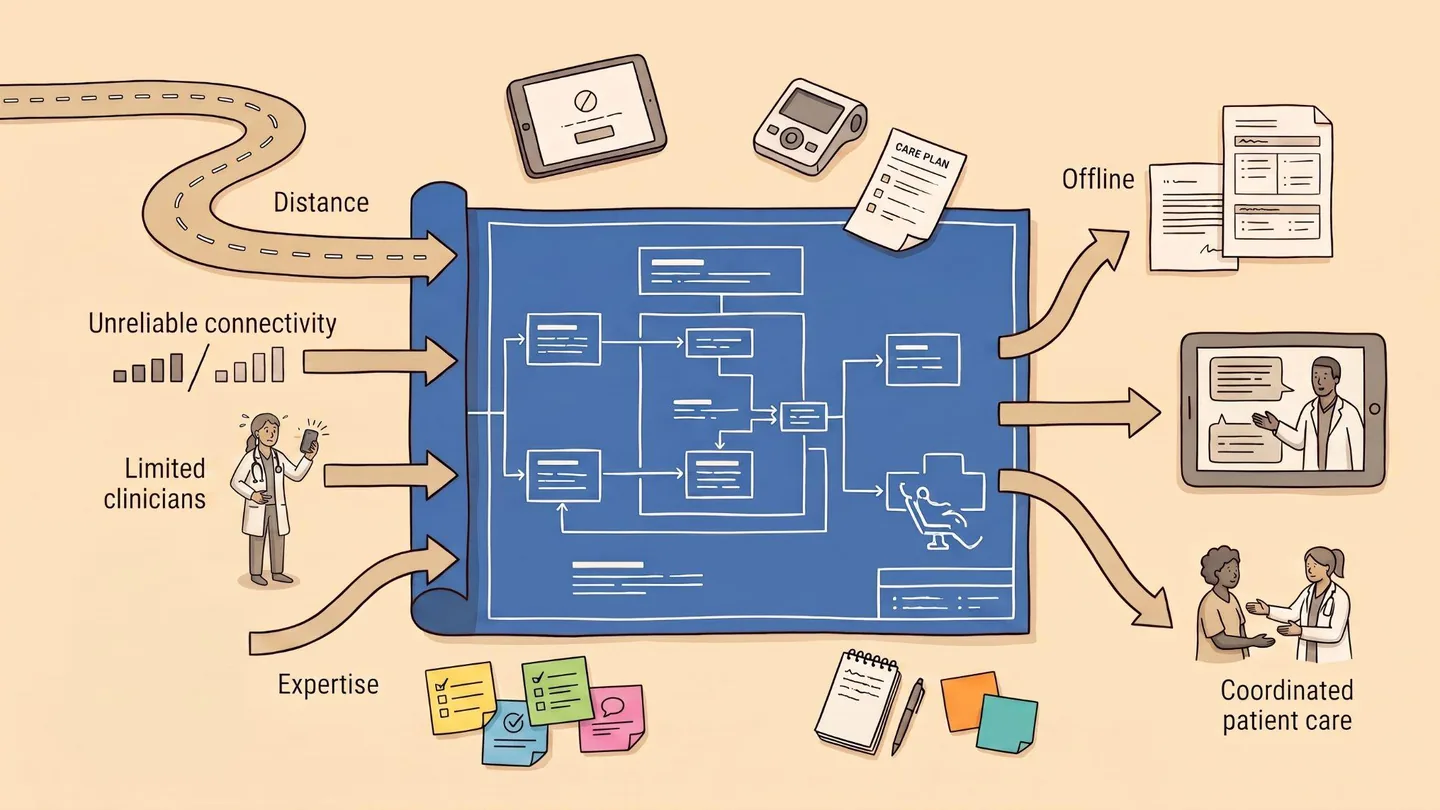
Most start with a Blueprint that maps the care model, the integrations and the build plan, then move to an MVP with real patients. These are common starting points, not rules.
The riskiest parts of a telehealth platform are rarely the video. They are the integration that takes four months instead of two weeks, the state licensing rules nobody wrote down, and the night shift that won't adopt a tool that slows them down. A Blueprint pulls those forward so the build plan reflects them.
NeverAlone followed this path: a short pilot with one population, then each new care setting added because the last one worked. See healthcare product development for the full path.
Common starting points for a virtual care platform
| Starting point | When it fits | What you get | Typical time |
|---|---|---|---|
| Blueprint | A new platform, or replacing a telehealth tool that no longer fits | Care journey, triage and routing rules, integration plan, architecture and a build plan your board can approve | 4 to 6 weeks |
| MVP | The care model is clear and you need real patients on it | A working platform for one population, built on production foundations | 8 to 16 weeks |
| Full build | The pilot worked and you're adding settings, states or customers | More care settings, integrations, reporting and multi-tenant support | 3 to 12 months |
| Run or transfer | The platform is live | 24/7 operations with L2/L3 support, or a planned handover to your team | Ongoing |
Virtual care platforms we built and run
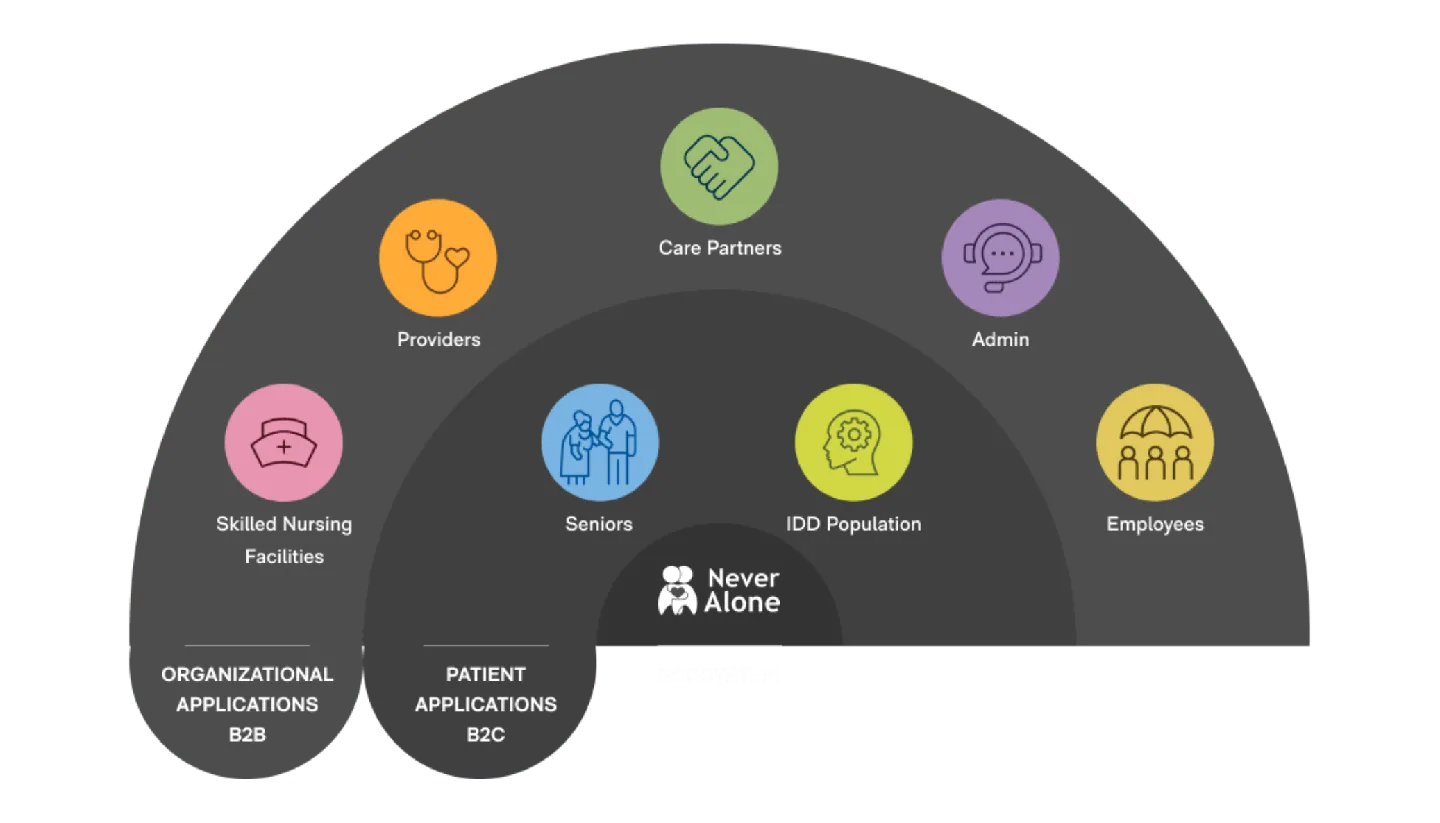
NeverAlone · CommuniCare
90-day MVP to 30,000 patients
A 24/7 virtual care platform that started as a tablet for seniors and now runs across six states. We still operate it.
See the work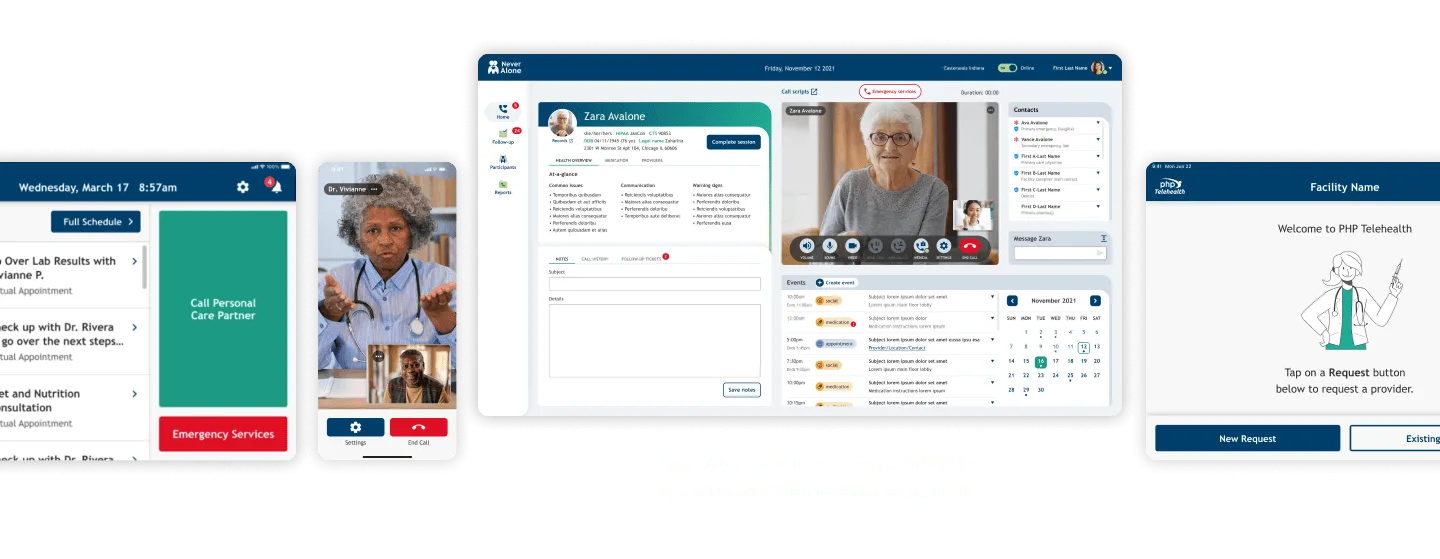
NeverAlone operations
100,000+ calls a year
A licensed provider in under 3 minutes, around the clock, with a 96% treat-in-place rate.
See the work
HealthContext.AI
Note time from 45 minutes to 5
An ambient AI scribe running inside NeverAlone, documenting telehealth calls for clinician review.
See the workTrusted by healthcare leaders.
“I have worked with many technology teams during my career, and Digital Scientists is one of the best. They take the time to understand the customers' needs, deliver innovative solutions, are always professional, and work with your team as a true partner to achieve success.”

Amy Severino
Chief Innovation Officer, CommuniCare Health Services
“NeverAlone has transformed how we deliver care at CommuniCare Health Services, enabling us to provide better patient care and achieve stronger clinical outcomes.”

Dr. Matthew Wayne
Chief Medical Officer, CommuniCare Health Services
Related services
Contact center and telephony
Call routing, queues, E911 and phone access for care teams.
Contact center and telephony →Behavioral health and SUD
Software for behavioral health and substance use treatment.
Behavioral health and SUD →Post-acute and senior care
Where NeverAlone started: skilled nursing and senior living.
Post-acute and senior care →Healthcare integrations
EHR, FHIR, data and HIPAA cloud.
Healthcare integrations →Platform operations
We run what we build, or hand it over.
Platform operations →

Questions about telemedicine and virtual care platforms
What is a virtual care platform, and how is it different from telehealth?
A virtual care platform is the connected system that delivers care outside the clinic, hospital or facility. Telehealth is one part of it: video and messaging visits. A full virtual care platform also includes remote patient monitoring, triage and care-team consoles, AI that drafts notes and flags what needs attention, and integration with the EHR, payer and care team. Buying a video tool is not the same as building a virtual care platform.
Should we build or buy a telehealth platform?
Buy if video visits add to in-person care and a licensed tool fits your workflow. Build when virtual care is the product or a core service line: when you need your own triage and provider routing, integration with your EHR and devices, data in your own cloud account, or a platform you sell to others. Many clients settle the question in a Blueprint before committing either way.
Can patients join by phone without an app?
Yes, if the platform is built for it. We design for the device the patient has. NeverAlone residents use a one-touch tablet with no app to download, no username and no password. For people on an ordinary phone line, the same video stack (AWS Chime) supports joining a visit by audio, so a phone caller and a provider on video can share one visit. We scope phone access in the Blueprint, alongside dial-in numbers and call routing.
How do you handle 42 CFR Part 2 for SUD telehealth?
We design for it from the Blueprint. 42 CFR Part 2 adds federal rules on top of HIPAA for substance use disorder treatment records, chiefly patient consent before most disclosures and limits on redisclosure. We capture and store consent per patient, keep Part 2 records segmented so they are shared only where consent allows, and log every access. We sign a BAA, and our security plan is mapped to NIST CSF 2.0.
Which video technology do you use?
We build video and voice on the AWS Chime SDK, running inside a HIPAA-eligible AWS account under a BAA, with Bandwidth for E911 emergency calling and Twilio for text messages and one-time codes. That stack carries NeverAlone's 100,000+ calls a year. If you already run another video vendor, we can build around it.
Can it connect to our EHR?
Yes, if it has an API, a standard interface or a reliable export. PointClickCare and Netsmart (GEHRIMED) run in production on NeverAlone, including matching patients across EHRs. We've worked with Epic in a test environment. Where the EHR supports FHIR we use it, and where it doesn't we build custom data exchange, planned before the build starts.
What about multi-state licensing?
The platform handles it. We build provider networks that track each provider's state licenses and route a call only to providers certified for that patient's state. NeverAlone works this way across six states.
Do you run it for us?
Yes, for platforms we build. We handle monitoring, releases, security updates and L2/L3 support, while your team or a clinical partner takes first-line questions. NeverAlone has run 24/7/365 since March 2021. When you're ready to own it, we hand over the code, the accounts and the runbooks on a build-operate-transfer plan.
Tell us about the product you want to launch
No commitment. No sales deck. We respond the same day, and you talk to senior leadership.
NeverAlone started as a 90-day MVP with us. It now serves 30,000 patients across six states.