
Healthcare AI Development on Your Data. Yours to Own.
Digital Scientists builds healthcare AI that runs in production on your data, and you own it. On new builds it runs inside your own AWS account, a person approves every output, and every output is logged. We start with one workflow and the number it has to move: MDS assessments, risk adjustment coding, clinical notes or a back-office queue. On CommuniCare's MDS platform, that's $10M+ recovered to date and $24M+ in forecast PDPM revenue. Most clients start with a Blueprint or two weeks of Build with Us.
Updated

Recovered to date on CommuniCare's MDS platform
Forecast PDPM revenue from the same MDS platform
RAF improvement at 90%+ accuracy, 2023 to 2024
Note time with HealthContext.AI






Where does AI pay back first in healthcare?
In high-volume, rules-heavy work where a person already reviews the result: MDS assessments, risk adjustment coding, clinical notes and reading device data. Those are the four places our builds have moved a number in production.
The pattern repeats. Pick one workflow with real volume. Name the number it should move: revenue, minutes or accuracy. Put the model's suggestion in front of the person who already does the work, with the source attached, so they decide faster and miss less. Then measure it against the old way.
Each row below is a system we built and put into production on real patient data. The results are in the case studies further down. Workflows with no clear number, or where nobody reviews the output, come later. See when to wait.
Where AI pays first, and where we've proved it
| Workflow | What the AI does | The number it moves | Where it runs |
|---|---|---|---|
| MDS assessments in skilled nursing | Scans PointClickCare data for 200+ clinical events that change an assessment and flags each one for the MDS coordinator, with the source documentation attached | PDPM revenue the facility has earned and documented | CommuniCare MDS, in production since April 2024, then handed to CommuniCare's own team |
| Risk adjustment (RAF/HCC) coding | Read EHR and prior-year claims data and suggested diagnosis codes, each linked to its evidence, for a coder to accept, change or reject | RAF accuracy and the revenue tied to it | CommuniCare risk adjustment, 2023 to 2024: 20K+ patients, 7 states, 245 providers |
| Clinical documentation | Transcribes the visit and drafts the note and summary for the clinician to review and sign | Minutes per note | HealthContext.AI, our own product |
| Remote anesthesia monitoring | A computer vision model reads vital signs off any brand of OR monitor and sends them to the anesthesiologist's phone | Accuracy of the vitals the clinician sees away from the room | Guardian: 99.9% transcription accuracy |
Common starting points, not rules. Every row has a person approving the output.
Why trust Digital Scientists with AI on patient data?
Because we've built healthcare AI and run it on real patient data for more than ten years. We're not learning healthcare on your dime.
A senior US team in your time zone, amplified by AI for throughput and quality, takes each system from messy data to a measured outcome. One team, concept to production, through all ten steps of the method below. We design with your clinicians, coders and coordinators, as partners rather than a vendor working from a spec.
Integration is where most healthcare AI stalls, so we start from integrations already running: PointClickCare and Netsmart (GEHRIMED) in production, Epic tested in a sandbox. Once a system is live, we run it with L2/L3 support or hand it to your team on a build-operate-transfer plan, as we did with CommuniCare's MDS platform. What the system learns from your data stays yours.
Building AI
Products shipped since 2007
PointClickCare and Netsmart (GEHRIMED) in production
Build-operate-transfer, or L2/L3 support on what we built
What rules does every AI system you build follow?
Six, on every build: your cloud account, your data trains nothing else, a person approves, accuracy on your cases, every output logged and a BAA first.
AI is a method, and in healthcare a method needs rules. Under them sits the security posture we use on all our healthcare app development: encryption at rest and in transit, role-based access, PHI de-identification for model training and a plan mapped to NIST CSF 2.0. The AI sits inside the tools clinicians already use, with no separate login and no duplicate entry. See security and PHI.
- Your cloud account. New builds run inside your own AWS account through Amazon Bedrock, including Claude, covered by your BAA with AWS.
- Your data trains nothing else. Bedrock doesn't train on your prompts or outputs. Any model we tune on your data is yours.
- A person approves. A clinician, coder or MDS coordinator approves each output before it reaches a chart, a claim or a patient.
- Accuracy on your cases. We test on your historical cases before go-live and after. On MDS, we checked each PDPM case-mix group against PointClickCare.
- Every output logged. What the model saw, what it suggested, the source it cited, the model version and what the reviewer did.
- A BAA first. We sign a BAA with every covered entity before we touch PHI, plus a security addendum for each client.
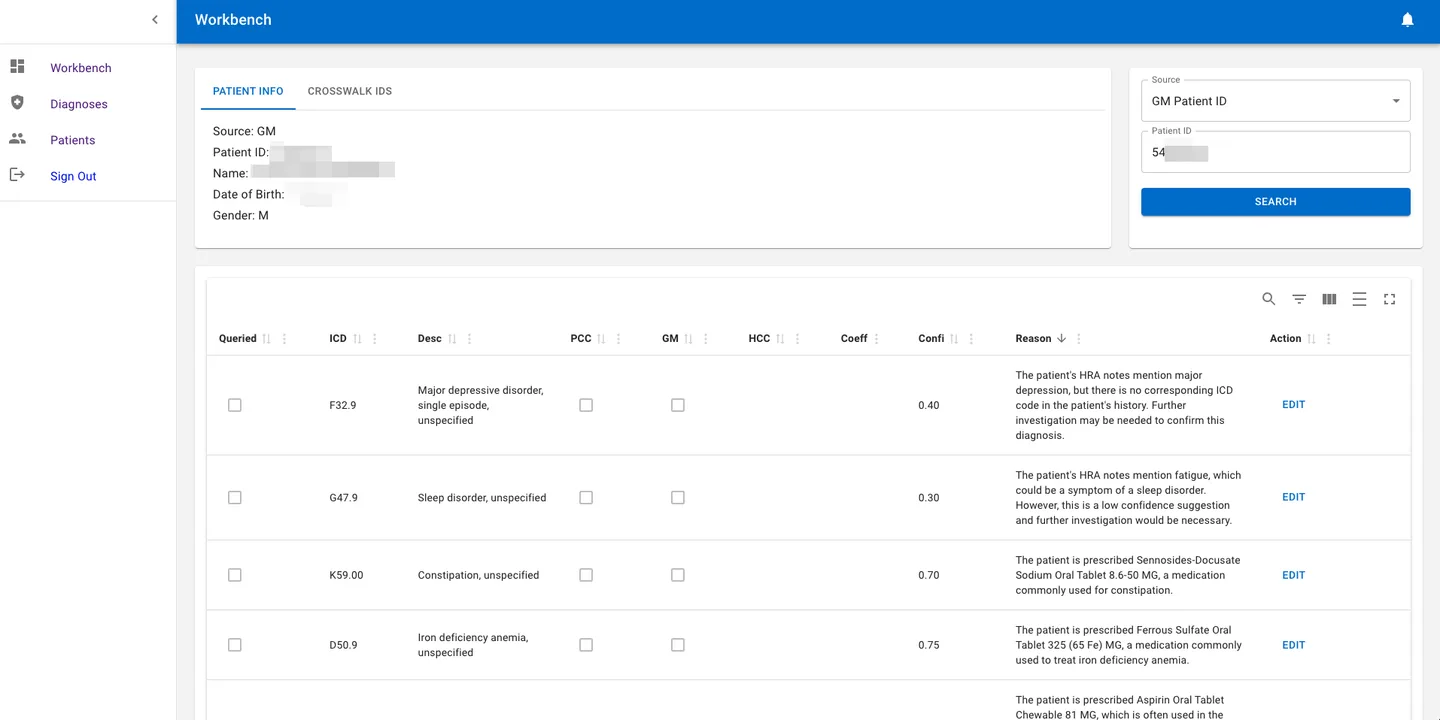
The coder workbench from the risk adjustment system we built (2023 to 2024). The AI suggests each code with its evidence and a confidence score, and a certified coder accepts or edits it. That's the rule in practice: a person approves every output.
Ten steps, from idea to measured results
Most AI projects stall after the demo: at integration with the EHR and claims systems, staff training and rollout. Those are steps 5 to 8, and we do them too. Our risk adjustment AI went from pilot to a $10M+ improvement at 90%+ accuracy.
Phase I
Discover
What should AI do?
Data Foundation
Assess & structure your data landscape
Co-Design
On-site discovery with care teams
Phase II
Experiment
Does the AI work?
Responsible AI Build
Model trained on your data, bias tested
EHR Integration
Connected to your systems, validated
Phase III
Engineer
Make it real.
Production Build
Scalable, monitored, HIPAA-compliant
Systems Integration
EHR, claims, devices, data pipelines
Change Management
Training & adoption with clinical staff
Production Deploy
Phased rollout with monitoring
Phase IV
Optimize
Make it better.
KPI Accountability
Measure outcomes, prove ROI
Continuous Improvement
Knowledge transfer or ongoing support
What kinds of healthcare AI do you build?
Three technologies applied to eight kinds of work. AI that supports clinical decisions, machine learning that predicts outcomes from your own history, and NLP that turns clinical text into coded data.
Data comes first: feeds from EHRs, medical devices and telehealth platforms, cleaned so models get reliable inputs. NLP pulls structured data from clinical notes, discharge summaries and pathology reports. Machine learning flags at-risk patients, and every recommendation links to the source data, so compliance teams and clinicians can check it. Agents are worth building only where a queue of routine work exists and someone can check the result.
Each area has its own page: AI agents, ambient scribes, RAF and HCC coding, MDS and PDPM, revenue cycle AI and clinical decision support. Still deciding? Our healthcare AI guides lay out ten frameworks for AI ROI, including clinical trial patient matching.
Back-office AI agents
Intake, eligibility, document routing, follow-ups
Ambient scribes
Visit transcribed, note drafted for the clinician to sign
RAF and HCC coding
Code suggestions linked to evidence for coders
MDS and PDPM
Assessment recommendations on PointClickCare data
Revenue cycle AI
Prior authorization prep, denial management, claims follow-up
Clinical decision support
Real-time suggestions at the point of care, each with its source
Predictive risk stratification
High-risk patients flagged before adverse events
Readmission prevention
At-risk patients flagged for follow-up and care coordination
How do you build clinical decision support clinicians trust?
Show fewer alerts, attach the evidence to each one, and leave the decision with the clinician. Clinical decision support (CDS) is software that puts patient data and clinical rules in front of a clinician at the moment of a decision. It earns trust when it saves time and is right often enough that people stop clicking past it.
Alert fatigue is how most CDS fails. Alerts and dashboards show up outside the workflow, most of them are noise, and clinicians learn to dismiss all of them. We build the other way: a short list of suggestions inside the tool the team already uses, each one linked to the note, lab or medication it came from.
That's how our builds for CommuniCare work. The MDS platform scans PointClickCare data for 200+ clinical triggers and flags each change for the MDS coordinator with its source attached, taking review from 3 to 4 hours per assessment to roughly 60 seconds per patient. The risk adjustment engine suggested each diagnosis code with its evidence and a confidence score, and ran at 90%+ accuracy. In both, a person on staff reviews every suggestion before it reaches a chart or a claim.
What makes clinical decision support get used
| What clinicians need | How we build it | Where we've done it |
|---|---|---|
| Fewer, better alerts | Flag only what changes a decision, inside the existing workflow, with no separate dashboard | MDS platform: 200+ clinical triggers scanned, only changes that affect the assessment flagged |
| The evidence, not just the answer | Every suggestion links to the note, lab or medication behind it | Risk adjustment: each code linked to its evidence, 90%+ accuracy |
| A person decides | A clinician, coder or coordinator approves; nothing writes to a chart or a claim on its own | Every build, with every suggestion and decision logged |
| Proof on your patients | Tested on your historical cases before go-live, then accept, change and reject rates tracked after | MDS: each PDPM case-mix group checked against PointClickCare |
Common patterns, not rules. Every row has a person on staff reviewing the output.
When should you wait on AI?
When the data isn't ready, when nobody owns the workflow, or when there's no number to move. In any of those cases, a model adds cost and risk before it adds value, and we'll tell you so.
We say it in the first conversation. Each signal has a fix, and the fix is usually work you'd need anyway. This is the healthcare AI consulting side of what we do: deciding what to build now and what to leave for later.
Most of the time the answer isn't no. It's not yet, plus the one step that gets you there. These are common patterns, not rules; see ways to start.
The data isn't ready
Key fields live in scanned PDFs, free text or a system nobody can export from, and patients carry more than one ID. Fix the data first with a data foundation. On CommuniCare's risk adjustment work, cleaning up patients with more than one Medicare ID came before any model.
Nobody owns the workflow
No one can approve a change to how coordinators, coders or nurses work, and no one has agreed to review the output. Name an owner and a reviewer first. Without both, the output goes unused.
There's no number to move
The goal is "use AI" and nobody can say what should go up or down. Pick the workflow and the metric first. A Blueprint does that in four to six weeks, with the cost and the expected return.
Most healthcare AI relationships start small.
Three common starting points. The smallest is two weeks with a senior architect in your systems. The largest is a production system deployed in your environment, integrated with your EHR.
Build with Us
$10K
2 weeks
A senior architect builds in your systems, on your data, on one well-defined use case. Two weeks and $10K is usually enough to find out whether it can be done.
Start Build with Us →The Blueprint
From $25K
4 or 6 weeks
An EHR-integrated architecture, cost model, compliance plan, and ROI projection. Build with us, hand it off, or use it to make the build-or-buy call.
Get a Blueprint →The MVP
$75K to $250K
8 to 16 weeks
A production AI system running on your data, integrated with your EHR, HIPAA-compliant from day one. Your team trained on it. You own the IP.
Build an MVP →Production-Grade AI Infrastructure
LLMs & NLP
Claude on Amazon Bedrock, OpenAI GPT-4 and Whisper, LangChain, custom fine-tuned models, clinical NER
Machine Learning
PyTorch, TensorFlow, scikit-learn, XGBoost, SageMaker, custom ML pipelines
Cloud & Infrastructure
AWS, Azure and Google Cloud, HIPAA-eligible services, VPC isolation, auto-scaling
Data & Integration
HL7 FHIR, CCDA, X12 EDI, Apache Airflow, Spark, custom ETL pipelines
EHR Platforms
PointClickCare and Netsmart (GEHRIMED) in production, Epic tested in a sandbox, custom API connectors
Languages & Frameworks
Python, Node.js, React, React Native, Ruby on Rails, PostgreSQL
Healthcare AI in production
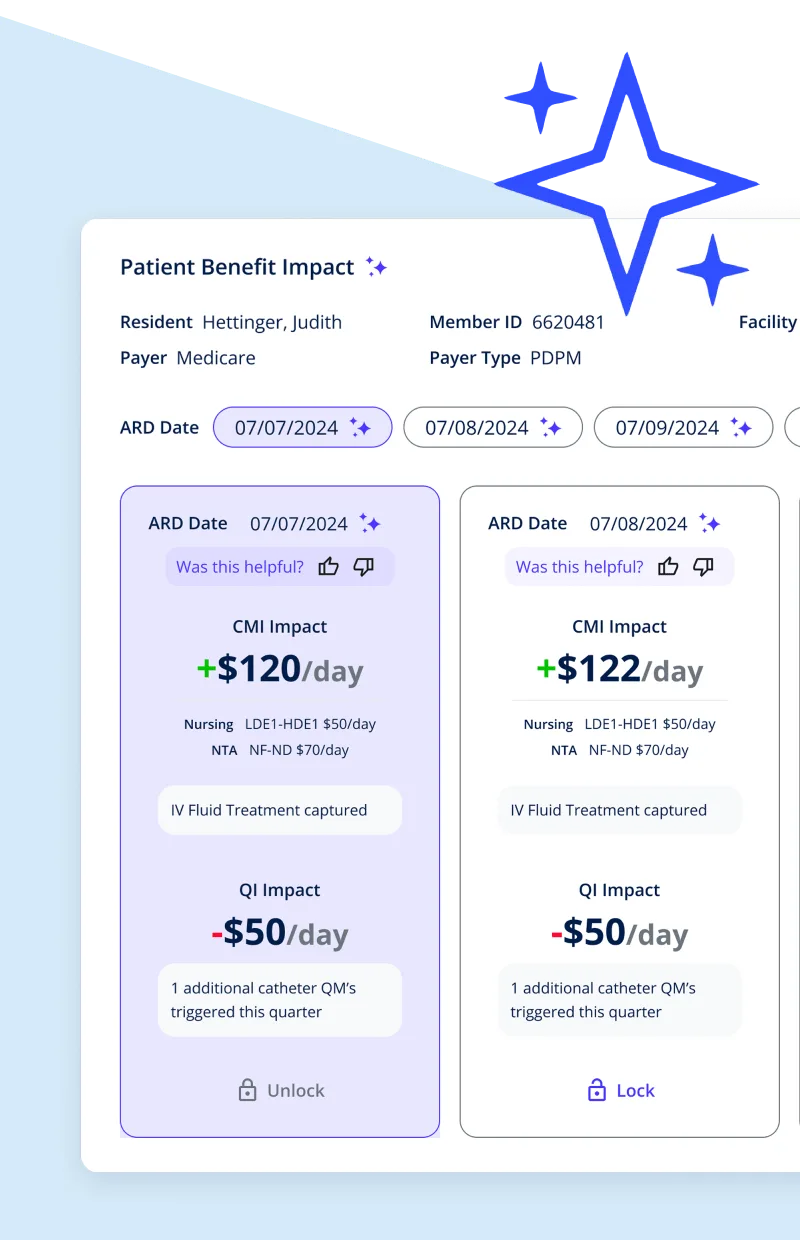
MDS · CommuniCare
$10M+ recovered to date
Recommendations on 200+ clinical events in PointClickCare data for MDS coordinators, plus $24M+ in forecast PDPM revenue. Built from April 2024 and handed to CommuniCare's own team.
See the work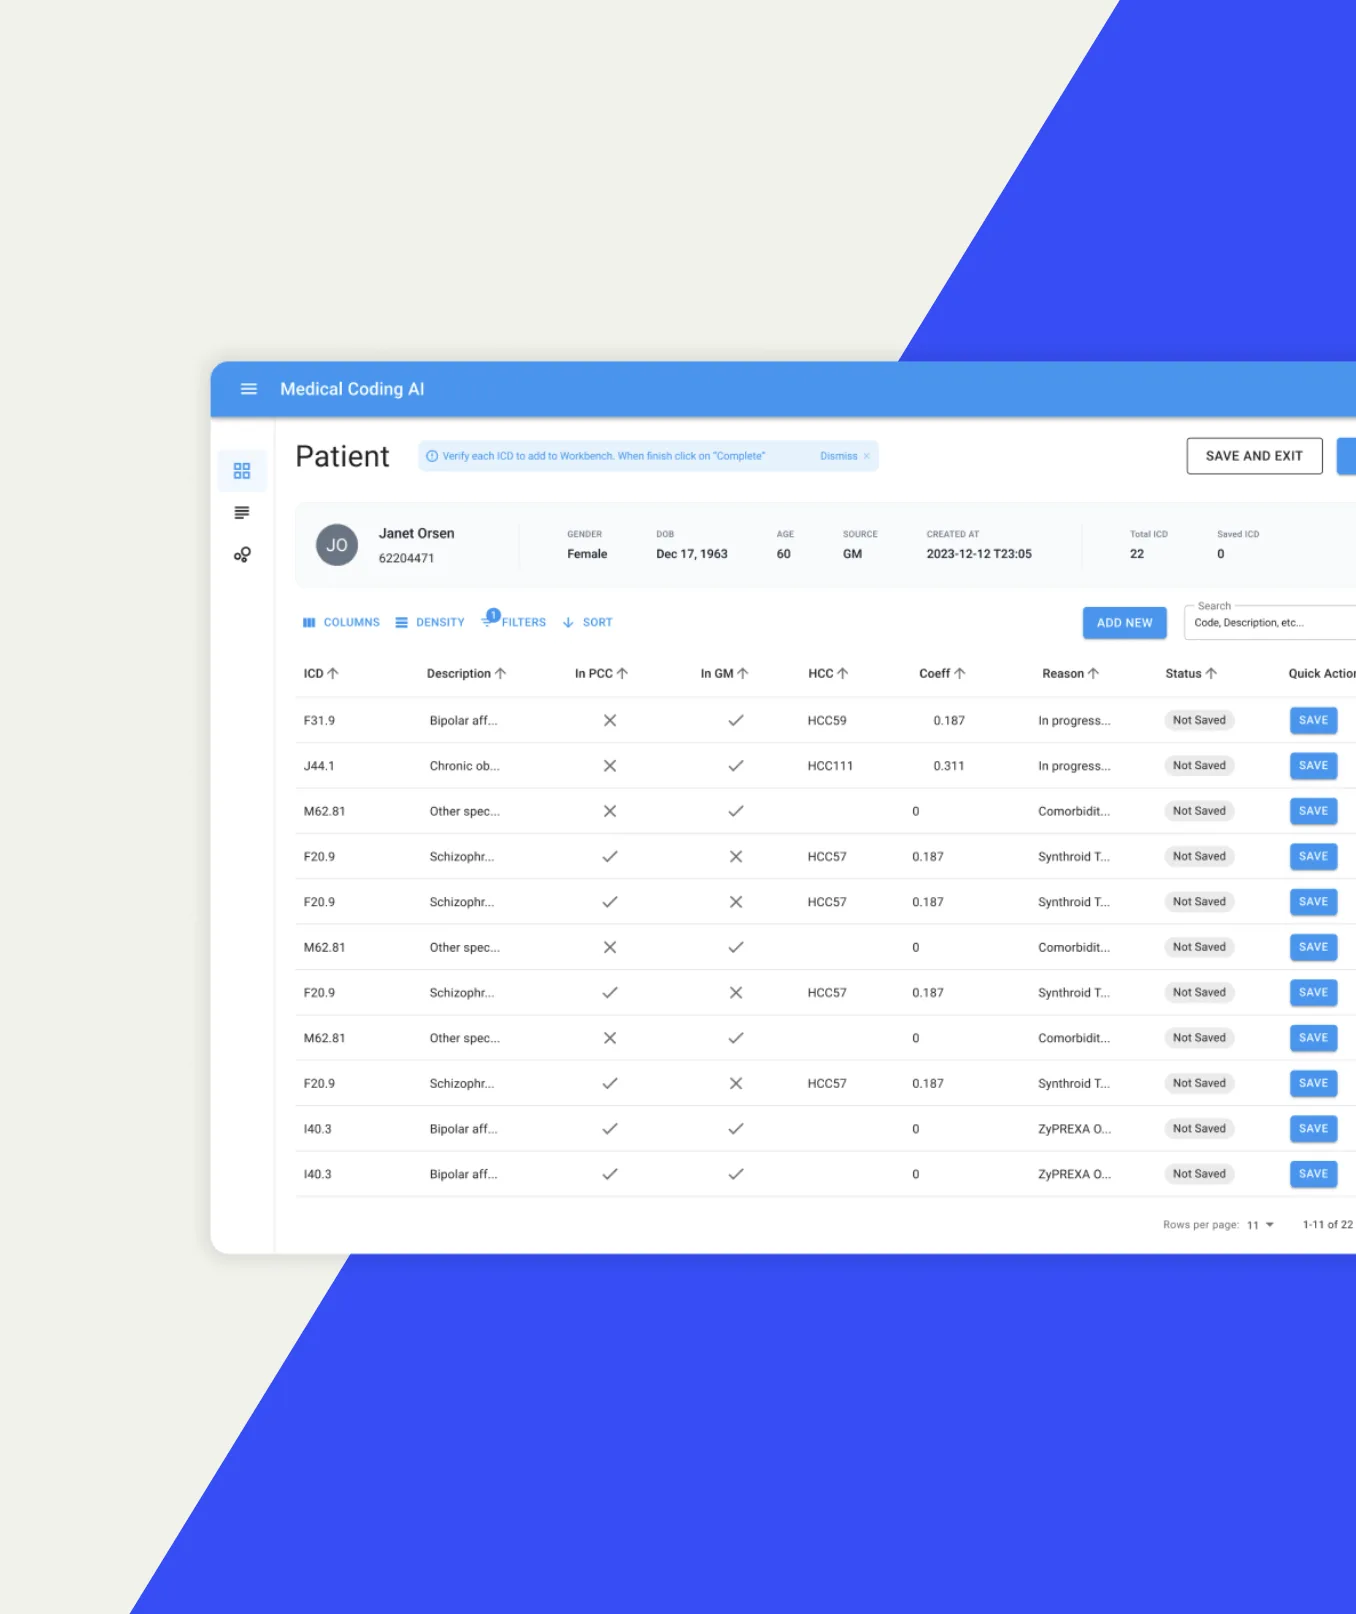
Risk adjustment · CommuniCare
$10M+ RAF improvement
Coding suggestions at 90%+ accuracy, 2023 to 2024, each code linked to its evidence. Physician feedback fed each model update.
See the work
HealthContext.AI
45 to 5 minutes per note
Our own ambient documentation product, built on Whisper, Amazon Comprehend Medical and GPT-4. The clinician reviews and signs every note.
See the workTrusted by healthcare leaders.
“By applying a robust machine learning model to our app, DS helped us create a scalable and accurate solution to improve the operating room experience for the anesthesia team and the patient. They are true collaborators.”

Justin Scott, M.D., FASA
CEO, Vigilant Medical Solutions
“The team at Digital Scientists was a huge help in not only developing our analytics platform, but understanding the competitive space and defining our true value proposition for our customers.”

Justin Davis
CEO, Congruity Health
Related healthcare work
Healthcare data engineering
Clean feeds, patient matching and the data foundation a model needs.
Healthcare data engineering →EHR integration
PointClickCare and Netsmart (GEHRIMED) in production, Epic tested in a sandbox.
EHR integration →Healthcare security and PHI
BAAs, a security plan mapped to NIST CSF 2.0 and per-client addenda.
Healthcare security and PHI →Platform operations
We run what we build, or hand it over on a build-operate-transfer plan.
Platform operations →Software as a medical device
Built to design controls, with a quality partner for the regulatory file.
Software as a medical device →AI development services
Custom AI, machine learning and agent development beyond healthcare.
AI development services →Latest thinking on healthcare AI
Common Questions About Healthcare AI
What is healthcare AI development?
Healthcare AI development is the practice of building custom artificial intelligence, machine learning, and natural language processing solutions for healthcare organizations. Unlike off-the-shelf AI tools, custom healthcare AI is trained on your data, integrated with your EHR, and designed for your specific clinical workflows. Applications include clinical documentation automation, RAF/HCC coding optimization, predictive risk stratification, revenue cycle automation, and MDS/PDPM optimization.
Does our data train your models?
No. Your data doesn't train any model for anyone else. On new builds, models run inside your own AWS account through Amazon Bedrock, and Bedrock doesn't use your prompts or outputs to train its foundation models. When we tune or train a model on your data, such as a risk model built from your own history, that model is yours. It runs only in your environment and stays with you.
Which models do you use?
The simplest one that does the job. For language work on patient data, we use Claude through Amazon Bedrock inside your AWS account. Plenty of problems don't need a large language model. Our risk adjustment engine was mostly SQL rules, with a generative model for about a fifth of the analysis. Guardian reads OR monitors with a computer vision model trained on more than a million images. We choose per workflow and write down why.
How do you measure accuracy?
On your own cases, against the answer your experts would give. Before go-live we run the system on historical cases your team has already worked and compare the results. On CommuniCare's MDS platform, we checked each PDPM case-mix group against what PointClickCare calculates. After go-live we track how often reviewers accept, change or reject each suggestion. Risk adjustment ran at 90%+ accuracy, and physician feedback fed each model update, which is reviewed before it reaches production.
What if the AI is wrong?
A person catches it before it matters. Every output goes to a clinician, coder or MDS coordinator who approves it, with the source documentation linked so they can check it quickly. Nothing writes to a chart or a claim on its own. Every suggestion and every decision is logged, so we can trace a wrong answer to its cause, fix it and test the fix on your cases before it ships.
Why do so many healthcare AI pilots fail?
Most healthcare AI pilots fail because they solve a technical problem without solving the workflow problem. The AI works in a demo but doesn't integrate with the EHR, doesn't fit how clinicians actually work, and can't handle the messy reality of production healthcare data. Digital Scientists delivers all 10 steps from data foundation through production deployment and continuous improvement, not just steps 1 through 4.
How long does it take to build custom healthcare AI?
Digital Scientists moves from concept to production in 8 to 16 weeks using a 4-phase methodology: Discover (data foundation, co-design with care teams), Experiment (responsible AI build, EHR integration), Engineer (production deployment, clinical change management), and Optimize (knowledge transfer, outcome measurement). More complex engagements may extend the Engineer phase, but we prioritize getting a working system into clinician hands quickly.
What is the ROI of healthcare AI?
Digital Scientists clients have seen measured returns from healthcare AI in production. Specific examples: $10M+ in RAF improvement at 90%+ accuracy across 20K+ patients, $10M+ recovered to date and $24M+ in forecast PDPM revenue from MDS optimization, and clinical documentation time reduced from 45 minutes to 5 minutes per visit. The key is targeting high-impact use cases where AI delivers hard dollar returns within the first calendar year.
How do you keep healthcare AI HIPAA compliant?
HIPAA compliance is built into every AI solution from day one. This includes encryption at rest and in transit, role-based access controls, full audit trails, PHI de-identification for model training, BAA compliance with cloud providers, and audit-defensible AI where every recommendation traces to source data. See our approach to security and PHI.
What makes healthcare AI different from general AI?
Healthcare AI must handle regulated data (HIPAA/PHI), integrate with clinical systems (EHRs, claims platforms), operate in life-safety contexts where errors have real consequences, and produce audit-defensible recommendations. It requires domain expertise in clinical workflows, medical terminology, coding systems (ICD-10, CPT, SNOMED CT), and healthcare data standards (HL7 FHIR, CCDA, X12 EDI).
Can healthcare AI integrate with our existing EHR?
Yes. PointClickCare and Netsmart (GEHRIMED) are in production on platforms Digital Scientists operates. Epic is tested in a sandbox. For other EHRs we integrate via HL7 FHIR APIs, ADT feeds, and custom data exchange where the EHR supports them, and we can integrate with any system that has an API, a standard interface or a reliable export. AI that lives outside the clinician's workflow doesn't get used. We embed AI recommendations, alerts, and automation directly into the systems clinicians already work in: no separate login, no duplicate data entry.
What is a clinical decision support system?
A clinical decision support system (CDSS) is software that brings patient data, clinical rules and AI models to a clinician at the moment of a decision, as an alert, a suggestion or a summary. Digital Scientists builds CDS inside the EHR or the tool your team already uses, links every suggestion to its source and leaves the decision with a person on staff. Our MDS and risk adjustment work for CommuniCare follows that pattern.
Tell us where AI should be doing the work
No commitment. No sales deck. We respond the same day, and you talk to senior leadership.
Our risk adjustment AI delivered a $10M+ improvement at 90%+ accuracy and reviews patients 50x faster.